In short
Skin picking is not always a willpower problem. For some people, picking becomes a learned behavioral loop driven by texture, sensory discomfort, emotion, fixation, environmental cues, or automatic behavior. Caring for the resulting skin means supporting physical healing while also recognizing when the behavior itself needs attention beyond skincare.
Skin picking can range from an occasional habit to a recurrent, difficult-to-control behavior that causes tissue damage, distress, or interference with daily life. Dermatillomania - clinically known as excoriation disorder - sits at the intersection of psychology and skin, where sensory triggers, emotions, automatic behaviors, environmental cues, and existing skin concerns can reinforce a cycle of picking and healing. Understanding that cycle helps move the conversation away from "just stop touching it" and toward understanding what the behavior may actually be doing for the person.
I want to start this Skin Journal a little differently.
Because this one is personal.
Both Sunni and I have struggled with skin-picking behaviors for essentially as long as we can remember.
They just don’t look the same.
For Sunni, It’s primarily her face, arms, blemishes, and lesions.
For me, it’s always been my lips and cuticles–and when I struggled with acne, absolutely my acne lesions too.
And if you’re someone who picks your skin, you probably know exactly what I mean when I say sometimes you don’t even realize you’re doing it.
Your hand just…
Finds the spot.
A rough cuticle.
A tiny bump.
A piece of dry skin on your lip.
A scab.
A blemish that feels like it needs to come out.
Maybe you’re staring into the bathroom mirror with your fingers… or when I was desperate tweezers, completely focused on it.
Or maybe you’re sitting at your computer, watching TV, driving, reading, or thinking about something else entirely–and suddenly realize you’ve been picking for the last 4 hours.
Then comes the aftermath.
The redness.
The swelling.
The bruising.
The bleeding.
The spot that was barely visible, the lips that you worked so hard not to touch for a week become impossible not to notice.
And, of course:
“Why did I do that?”
So I don’t want this article to be another esthetician telling you:
“Just stop picking your skin.”
Thanks for stating the obvious!
It’s so much deeper than that, and this roots us back to the topic of psychology and skin.
I want to talk about why we pick in the first place.
Because sometimes skin picking isn’t simply a “bad skincare habit.”
Sometimes it’s psychological.
Sometimes it’s sensory.
Sometimes it’s fixation.
Sometimes it’s automatic.
Sometimes it’s coping.
Sometimes it’s emotional.
And for some people like me and Sunni, it can become a recognized mental health condition called excoriation disorder, commonly known as dermatillomania.
Let’s get into it.
First things first: what is dermatillomania?
The clinical term is excoriation disorder, or skin-picking disorder.
Dermatillomania is another name commonly used for it.
It’s classified among obsessive-compulsive and related disorders and involves recurrent skin picking that causes tissue damage, along with repeated difficulty stopping and clinically significant distress or impairment.
And this distinction matters a lot:
Picking your skin doesn’t automatically mean you have dermatillomania.
Most people have popped a pimple.
Pulled off a scab.
Picked at a hangnail.
That alone isn’t a psychiatric disorder.
The clinical concern is when the behavior becomes recurrent and difficult to control and begins causing meaningful physical damage, distress, or interference with someone’s life.
So not:
“I picked off a scab and moved on with my life.”
It’s:
I have been stuck in picking paralysis for 5+ hours and haven’t been able to move, get up, and my life is at a standstill when it is happening despite how much I am bleeding and in pain.
That is the real experience coming from someone with this condition. It is debilitating.
There’s also a larger family of behaviors called body-focused repetitive behaviors or BFRBs.
These can involve repetitive picking, biting, pulling, or scraping of the skin, hair, lips, cheeks, or nails.
So the behavior can exist across a spectrum.
And that’s something I really wish more people understood.
Because skin picking doesn't always look like picking acne
When people hear dermatillomania, I think they picture someone standing inches away from a magnifying mirror squeezing their face.
That can absolutely happen.
But skin-focused repetitive behaviors can involve:
The face.
Arms.
Legs.
Hands.
Feet.
Cuticles.
Scabs.
Healthy skin.
Bumps.
Lips.
Acne lesions.
And people may use their nails, fingers, teeth, tweezers, or other tools.
For me?
My lips and cuticles are the big ones.
And that’s important because sometimes people don’t even recognize those behaviors as skin picking.
You might think:
“I don’t pick my skin. I just bite the dry pieces off my lips.”
Or:
“I just can’t stand when my cuticles feel uneven.”
And suddenly you’ve been trying to make one microscopic rough edge “smooth” for 30 minutes.
Which brings us to one of the most important parts of this entire conversation.
Sometimes you’re not trying to hurt the skin.
You’re trying to fix it.
This is something I understand all too well.
There’s a bump.
An edge.
A flake.
A scab.
A piece of skin that feels different from everything around it.
And your brain notices it.
Then you touch it again, and again.
And suddenly there’s this overwhelming feeling that if you could just remove that one thing, the surface would finally feel smooth.
So you pick it.
Except now there’s another edge.
So you pick that.
Now it’s bleeding, now there’s a scab.
Tomorrow you feel the scab, and you need to remove the scab.
And the entire cycle has created its next trigger.
This is one reason telling someone: “Just don’t touch it.”
It’s like telling someone with depression to just “stop being depressed.”
You're missing what’s actually maintaining the behavior.
Skin picking can be sensory
This part fascinates me.
For some people, the trigger isn’t necessarily an emotion. It's a sensation.
Something feels wrong.
Rough.
Raised.
Uneven.
Dry.
Sharp.
Textured.
And the urge to correct it.
Research and behavioral treatment models for BFRBs specifically recognize sensory triggers–such as skin that feels unpleasant or “wrong”--as factors that can initiate and reinforce picking.
That’s why a microscopic bump that nobody else would ever notice can feel incredibly difficult to leave alone.
You’re not necessarily thinking:
“I’d like to damage my skin right now.”
Your brain is thinking:
That shouldn’t be there.
And picking temporarily resolves that sensory discomfort.
Until, of course, it creates more texture.
Sometimes it’s emotional
For other people, picking happens more during:
Stress.
Anxiety.
Frustration.
Boredom.
Sadness.
Overwhelm.
Or intense periods of concentration.
Some people experience increasing tension or an urge before picking and temporarily feel relief afterward. Others barely notice the behavior until they’ve already been doing it.
And that’s exactly why two people can engage in what looks like the exact same behavior for completely different reasons.
One person picks because they’re anxious.
Another because they’re bored.
Another because a bump feels intolerably uneven.
Another starts automatically whenever they’re sitting at their desk.
And one person may experience all of those patterns.
Focused picking versus automatic picking
This is another distinction I think people will recognize immediately.
Sometimes picking is extremely focused.
You go to the mirror.
You turn on the bright light.
Maybe the magnifying mirror comes out.
You find a lesion.
And now you’re locked in.
You’re inspecting.
Squeezing.
Searching.
Trying to "finish" something.
But picking can also be incredibly automatic.
You’re watching television and your fingers are scanning your arm.
You’re reading and suddenly you’re touching your cuticles.
You’re working and realize you’ve been biting your lip.
You’re on the phone and your hand keeps finding the same scab.
BFRBs can occur both intentionally and outside of conscious awareness, including during sedentary activities like studying, reading, working at a computer, or talking on the phone.
That distinction matters when we’re trying to change the behavior.
Because you can’t interrupt something you’re not even noticing.
And then comes the relief
This is where the behavior can become self-reinforcing.
You find the imperfection.
You pick it.
For a moment?
Relief.
Maybe the texture is gone.
Maybe the pressure from the blemish changed.
Maybe your hands finally feel satisfied.
Maybe picking distracts you from anxiety.
Maybe your brain simply got the sensory reward it was looking for.
And then… you look at your skin.
Now it’s red.
Maybe bleeding.
Maybe swollen.
And the relief gets replaced by:
Regret.
Embarrassment.
Frustration.
Or shame.
Then the wound heals.
A scab forms.
The scab becomes another texture.
You feel it.
And the cycle starts again.
That’s not a lack of willpower.
It’s a learned behavioral loop.
Now let’s talk about what happens to the skin.
Because this is where my aesthetician brain enters the conversation.
Every time we pick, squeeze, scratch, or dig at a lesion, we’re creating mechanical trauma.
We’re disrupting the epidermis.
Potentially damaging deeper tissue.
Increasing inflammation.
And interfering with the wound-healing process that was already happening.
Depending on how deeply and repeatedly someone picks, the consequences can include:
- Persistent erythema
- Prolonged healing
- Post-inflammatory hyperpigmentation
- Open wounds
- Crusting
- Infection
- Textural changes
- Scarring
In severe cases, excoriation disorder can produce significant tissue injury.
So yes…
The picking itself can become a skin condition we need to manage.
Picking acne deserves special attention.
This one is especially important to me because I’ve experienced it myself.
When you have acne, there’s already inflammation occurring inside the pilosebaceous unit.
And when you see that lesion sitting there?
Everything can feel like:
Get it out.
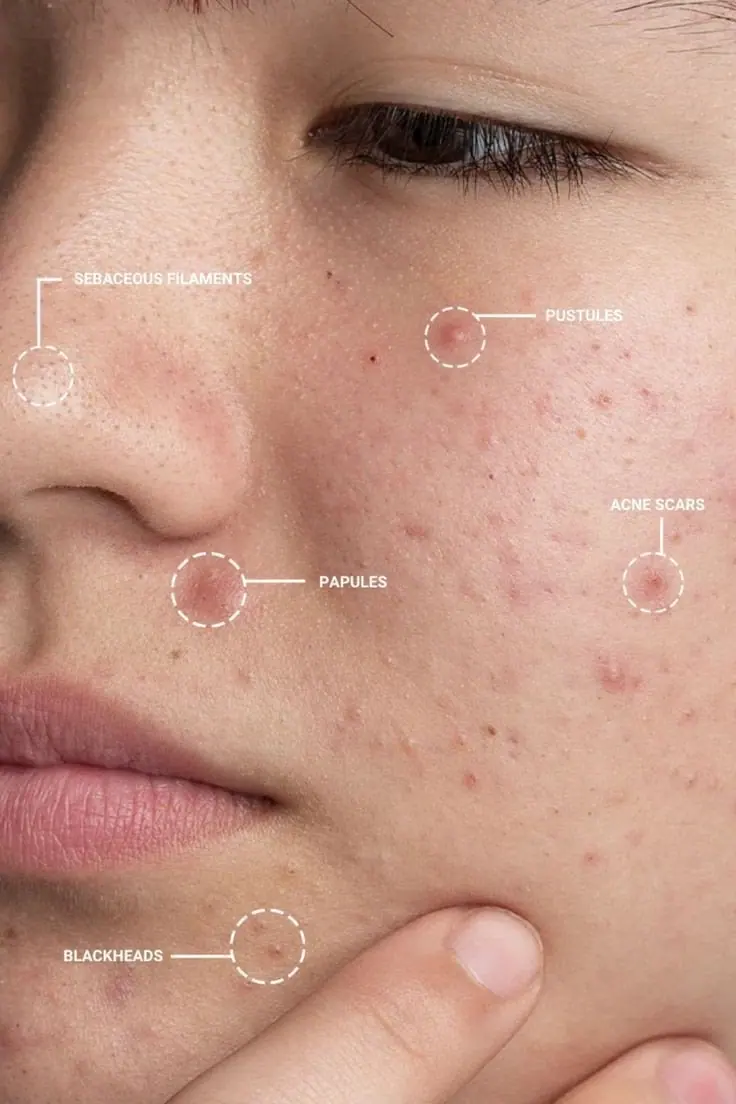
But squeezing and picking acne can increase tissue trauma and inflammation, prolong healing, and increase the risk of both discoloration and permanent scarring. This is why as professionals we advise against popping and picking acne.
And here’s the frustrating part.
Sometimes the lesion you were trying to make disappear overnight becomes the mark you stare at for six months.
I know.
That’s exactly why it’s so difficult.
Sometimes we create the thing that triggers us
This is the vicious part of the cycle.
Imagine you start with a tiny blemish.
You pick it.
Now it’s inflamed.
Then it crusts.
You feel the crust.
You remove it.
Now the wound reopens.
It heals again.
Another scab forms.
You pick again.
And eventually the original acne lesion may not even be the primary issue anymore.
We’re now dealing with repeated mechanical injury.
This is something I think is really important clinically.
If I’m evaluating someone’s skin and I see excoriated lesions, I need to distinguish:
What is the underlying skin condition?
And
What has been created or prolonged by manipulation.
Those aren’t always the same thing.
This is also why skincare alone may not solve the problem.
Imagine I create the perfect acne regimen for someone.
Their follicular congestion improves.
Inflammation decreases.
They’re developing fewer lesions.
Amazing.
But every tiny lesion that does appear gets repeatedly manipulated.
Now we’re still seeing redness.
Pigmentation.
Open wounds.
Scarring.
And prolonged inflammation.
At that point, adding another serum isn’t necessarily the missing piece.
We have to address the behavior surrounding the skin, too.
And that’s where psychology and aesthetics genuinely intersect.
No, telling someone to “have more self-control” isn’t treatment.
If you’ve struggled with this behavior, you’ve probably told yourself to stop hundreds of times.
“I’m not touching my face anymore.”
“I’m letting my lips heal.”
“I’m leaving this scab alone.”
Then two hours later… you’re doing it again.
That’s because established BFRBs can involve learned behavioral patterns, sensory reinforcement, environmental cues, emotions, and automatic behaviors. Evidence-based behavioral approaches therefore focus on understanding and interrupting those patterns–not simply demanding more willpower.
This is where Habit Reversal Training, or HRT, becomes particularly interesting.
What is Habit Reversal Training?
Habit Reversal Training is one of the most established behavioral approaches for BFRBs such as skin picking.
A major component involves increasing awareness of the behavior and then learning a competing response– something physically incompatible with picking that can be used when an urge or trigger happens.
For example:
Maybe you notice that you always pick while watching television.
Or your hand automatically goes to your face while you’re working.
Or you start scanning your skin whenever you’re anxious.
Simply identifying:
When does this happen?
Can be incredibly useful.
Because we’re moving from:
“Why can’t I stop?”
To:
“What reliably happens before I start?”
That’s a much more actionable question.
There’s also something called ComB
And I love the philosophy behind this because it’s so individualized.
Comprehensive Behavioral Treatment, or CombB, looks at the different factors contributing to your particular picking pattern.
Not everyone’s trigger is anxiety.
Not everyone’s trigger is texture.
Not everyone’s trigger is boredom.
So treatment shouldn't assume every person picks for the same reason.
ComB can examine sensory triggers, thoughts, emotions, motor patterns, and environmental situations to identify what is maintaining the behavior and build alternative responses around those specific triggers.
Sound familiar?
It’s basically the psychology version of something I say about skincare constantly:
Context matters.
And sometimes environmental changes can help.
This doesn’t replace professional treatment when someone has significant BFRB.
But understanding your riggers can help you make the behavior slightly harder and healing slightly easier.
Maybe that means:
Keeping nails shorter.
Covering a healing lesion with an appropriate hydrocolloid patch.
Removing the magnifying mirror that turns five minutes in the bathroom into forty-five.
Keeping tweezers somewhere less accessible.
Using a fidget or another competing hand activity during the situations when you automatically pick.
Keep cuticles appropriately moisturized so there are fewer rough edges begging for attention.
Using lip care that reduces cracking and loose skin if your lips are a major trigger.
These aren’t about punishing yourself or physically restraining your hands.
They’re about changing the environment surrounding an automatic behavior.
And importantly, behavioral treatment works best when strategies are matched to the reason you pick.
And please don’t put aggressive actives on freshly picked skin.
I know the temptation.
You picked a pimple.
Now you’re panicking.
So you grab:
Salicylic acid.
Bezoyl peroxide.
Retinoid.
Maybe an exfoliating toner for good measure.
And put everything directly onto the open spot because you need it gone.
But freshly excoriated skin is injured skin. Would you apply any of those listed ingredients to a fresh wound? No.
You’ve disrupted the protective barrier and this isn’t the moment I want to punish the area further.
Keep it clean.
Protect it appropriately.
Support wound healing.
And once the skin has re-epithilialized, we can return to whatever treatment is appropriate for the underlying concern.
Sometimes the most productive skincare step after picking is incredibly boring:
Leave it alone enough to heal.
Shame makes this conversation worse.
This is something I really want included in EPIARA’s philosophy around skin picking.
Because people hide this.
They cover the wounds.
They apologize to their aesthetician.
They say:
“I know. I know. I shouldn’t have picked it.”
And I never want someone sitting in front of me feeling like they need to confess what they did to their face.
Especially because…
I understand it.
Sunni understands it.
We aren’t standing on the other side of this conversation pretending like we don’t both struggle with this condition.
Skin picking can be incredibly frustrating.
But shame isn’t a treatment.
If anything, negative emotions can themselves become part of the behavioral cycle for some people.
So I would much rather understand:
What happened?
What were you doing?
What did the skin feel like?
Were you aware you were picking?
Was there something about the lesion that triggered you?
What happened afterward?
That’s information. And information gives us somewhere to go.
When should someone seek professional help?
If skin picking is causing recurrent wounds, infections, significant scarring, distress, shame, avoidance, interference with daily life, or repeated unsuccessful attempts to stop, it’s worth talking to a qualified mental health professional familiar with BFRBs.
Skin-picking disorder is treatable.
Behavioral therapies including CBT approaches, Habit Reversal Training, and ComB are used specifically for these behaviors.
Sometimes the best care involves both.
That’s not overreacting.
That’s treating the whole problem.
Why this matters as a provider
When I see picked skin, I don’t only see:
“Client noncompliance.”
I see information.
Maybe we’re dealing with acne.
Maybe there’s a sensory trigger.
Maybe the person is unconsciously scanning their skin.
Maybe they’re anxious.
Maybe the treatment plan is creating excessive flaking and giving them more things to manipulate.
Maybe they have an established BFRB.
Maybe they’re simply someone who occasionally picks blemishes.
Those situations aren’t interchangeable.
And my role as an aesthetician isn’t to diagnose a psychiatric disorder.
It’s to recognize when the behavior is affecting the skin, support the physical healing appropriately, modify the skincare plan when needed, and recognize when something falls outside of my scope.
Final Thoughts
Dermatillomania taught me something about skin that I don’t think I could have learned from a textbook alone.
Sometimes we know exactly what we’re doing to our skin…
And still struggle to stop doing it.
That’s important.
Because education alone isn’t always enough. Someone can understand the inflammatory cascade of acne perfectly and still pick a pimple.
I can understand wound healing and still catch myself picking at my lips or cuticles.
Knowing better doesn't automatically turn off a behavioral loop that has existed for years.
And that’s why I don’t think the answer to skin picking is:
“Just leave your skin alone.”
We need to understand what the behavior is doing for the person.
Is it sensory?
Automatic?
Emotionally regulating?
Triggered by an actual skin condition?
Usually, there’s more information hiding underneath the behavior.
And once again, we arrive at the same place I seem to arrive at with almost everything in skincare:
Understand first. Treat second.
Journal Note
This one feels different to write because I can’t separate myself completely from the topic.
Neither can Sunni.
We’ve both spent years telling ourselves some version of:
“Okay. I’m actually going to stop this time.”
In fact, before finishing this article I found myself picking at my lips and zoning out for 30 minutes telling myself that exact sentence.
Our picking doesn't even look the same.
Sunni tends to find lesions–her face, her arms, something she can see or feel and wants gone.
Mine always gravitated toward my lips and cuticles, and when I had acne, those lesions became targets too.
Different locations.
Different triggers.
Same strange experience of realizing that sometimes your hands seem to make the decision before the logical part of your brain gets involved, and sometimes even when it does that still isn’t enough.
And I think experiencing that has changed the way I look at picked skin professionally.
I don’t see a client who “ruined their skin.”
I see skin that’s injured and needs to heal–and sometimes a person dealing with something that another skincare product can’t fix.
We can treat the acne.
We can support the barrier.
We can protect the wound.
We can eventually address the pigmentation or scar.
But sometimes caring for skin also means recognizing when the thing affecting it isn’t really a skincare problem at all.
And I think there’s something really important about making room for that conversation here.
Because Skin Journals were never supposed to be only about products and skincare.
They’re about understanding the person wearing the skin.